


TL;DR
We recommend choosing clinical-to-commercial peptide CDMOs by verified small-batch GMP fit, synthesis and purification capability, analytical control, and accountable process transfer. This guide shows how we compare clinical, registration, and commercial readiness, evaluate complex-peptide controls, and build an RFI that avoids unsupported capacity claims.
We see peptide programmes become harder to manage when impurity separation and analytical control lag behind synthesis development. The EMA peptide guideline sets a 0.1% reporting threshold for peptide-related impurities, which makes early process knowledge relevant long after the first GMP batch.
Clinical-to-commercial peptide CDMOs are the partners that can accept a practical GMP clinical batch, establish the analytical control strategy, and transfer the same process into registration and commercial equipment with documented comparability. We recommend choosing on verified minimum batch, synthesis and purification fit, quality evidence, and change-control ownership, rather than a broad capacity claim.
In this guide, we explain how we assess stage fit, small-batch capability, complex-peptide controls, transfer readiness, and supplier-selection evidence for peptide API programmes.
Which Clinical-to-Commercial Peptide CDMOs Fit Each Stage?
At Aarise Pharma, we do not treat a supplier’s largest reactor as proof that it can support a clinical programme. A suitable partner must match the product’s required GMP quantity today, then show how its process, analytical methods, materials, and quality system will remain comparable as demand grows. Our commercial GMP suppliers guide can help buyers frame the commercial side of that review.
| Facility Model | Clinical Batch Fit | Registration Readiness | Commercial Readiness | Evidence We Request |
|---|---|---|---|---|
| Early Clinical Suite | Gram to low-kilogram GMP batches | Process-development report and analytical transfer plan | Defined route to later-stage equipment | Minimum practical batch and purified output |
| Integrated Network | Clinical production at a development site | Comparability protocol between sites | Commercial train within the same quality network | Written transfer responsibilities |
| Specialist Peptide Site | Sequence-specific synthesis and purification | Impurity map, stability, and reference standards | Capacity expansion or qualified commercial route | Relevant complex-peptide case evidence |
| General API Facility | May support selected peptide programmes | Peptide-specific CMC evidence required | Commercial campaign capacity must be verified | Proof of peptide purification and control strategy |
What Matters at the Clinical Stage?
We ask whether the site can make the required GMP quantity with a realistic charged scale, not merely whether it accepts a small purchase order. The supplier should identify expected crude yield, purified yield, chromatography loading, isolation method, release tests, and a credible clinical delivery sequence.
What Changes at Registration Scale?
Registration readiness requires more than a larger batch. We look for defined critical process parameters, an established impurity profile, phase-appropriate specifications, stability plans, and analytical methods that can transfer without losing selectivity. ICH Q11 frames drug-substance development around process understanding and the information expected in CTD quality documentation.
What Proves Commercial Readiness?
Commercial readiness means the manufacturing train, purification equipment, solvent handling, quality oversight, and supply chain have evidence behind them. We want a documented technology-transfer model, clarity on material and equipment changes, and written accountability if a commercial campaign introduces a new impurity pattern.
Which Peptide CDMO Handles Small Clinical Batches?
Small clinical batches should be defined by the final GMP API quantity needed for the study, not by vague labels such as small, pilot, or flexible. We start with projected patient count, dose, dosing interval, retest requirements, retains, reference standards, and formulation losses. That calculation helps us distinguish a feasible clinical campaign from an attractive but impractical capacity claim.
A supplier should disclose its minimum practical GMP batch, including minimum resin charge, expected final isolated quantity, purification loading, and whether the requested scale is compatible with its normal quality and release workflow. We also ask whether the clinical process is intended to survive transfer into larger equipment or whether it is only a temporary route. Our peptide buyer guide provides a useful procurement framework for documenting those questions.
For clinical-trial material, quality documentation still needs to support the product and its intended use. The EMA clinical guidance specifically includes synthetic peptides among the products covered by its investigational-medicinal-product requirements.
| Buyer Question | Why We Ask It | Strong Evidence |
|---|---|---|
| What is the minimum practical GMP batch? | It reveals whether a small programme fits the suite | Charged scale, expected final yield, and release plan |
| What is the smallest purified output? | Reactor volume does not equal final API quantity | Purification loading and isolation recovery |
| Can the same route scale? | A clinical route may not transfer cleanly | Written scale-up and comparability strategy |
| Who owns analytical transfer? | Method drift can obscure product changes | Protocol, acceptance criteria, and responsibilities |
| What changes after the clinical batch? | New materials or equipment may change impurities | Change-control and regulatory assessment process |
Our India sourcing benefits resource can support the broader procurement review while this guide keeps peptide-specific manufacturing evidence at its center.
Which Synthesis, Purification, and Controls Fit the Peptide?
The best route depends on sequence length, aggregation tendency, modification profile, required purity, annual demand, and how the product will be characterized. We assess solid-phase, liquid-phase, hybrid, recombinant, and conjugation approaches as technical choices, not interchangeable supplier checklist items.
How Do We Match the Synthesis Route?
Solid-phase synthesis can offer development flexibility, while liquid-phase and hybrid strategies may suit particular sequences and larger-scale economics. We ask how the chosen route controls coupling efficiency, deletion sequences, epimerization, deprotection, cleavage, and intermediate handling. For modified, cyclic, long, or aggregation-prone peptides, we require evidence that the supplier has considered route-specific risks.
How Do We Assess Purification?
Preparative chromatography is often the real production constraint because it determines loading, resolution, recovery, pooling, solvent demand, and cycle time. We ask for the proposed purification mode, critical-pair resolution, fraction-pooling rationale, desalting approach, and isolation process. Our GMP export guide helps connect those manufacturing details to the quality systems buyers should review.
Which Analytical Controls Cannot Be Generic?
We expect an identity strategy using orthogonal methods where justified, plus methods for assay, related substances, residual solvents, water, counterion, and other product-specific attributes. The EMA peptide rules recommend at least two orthogonal identification methods and highlight the risk of co-eluting peptide impurities.
What Should We Request for Difficult or High-Potency Peptides?
For complex or potent material, we request containment and cleaning rationale, exposure assessment, impurity-characterization plans, relevant stability work, and clear handling controls. We also want to know whether conjugation, disulfide formation, and reference-standard preparation occur within the same accountable quality system. Our API testing guidance can help teams translate these requests into a practical review list.
How Should a Clinical Process Transfer to Commercial Equipment?
A successful transfer starts before the clinical batch is made. We recommend building the commercial intent into the development plan by identifying critical material attributes, critical process parameters, in-process controls, impurity controls, analytical methods, and planned equipment changes from the outset. Our API testing guide can help teams prepare the analytical evidence needed for that planning.
The transfer package should explain what is known about resin, amino-acid building blocks, reagents, reaction conditions, purification loading, fraction selection, isolation, hold times, and stability. It should also define the acceptance criteria used to decide whether registration or commercial material remains comparable with clinical material.
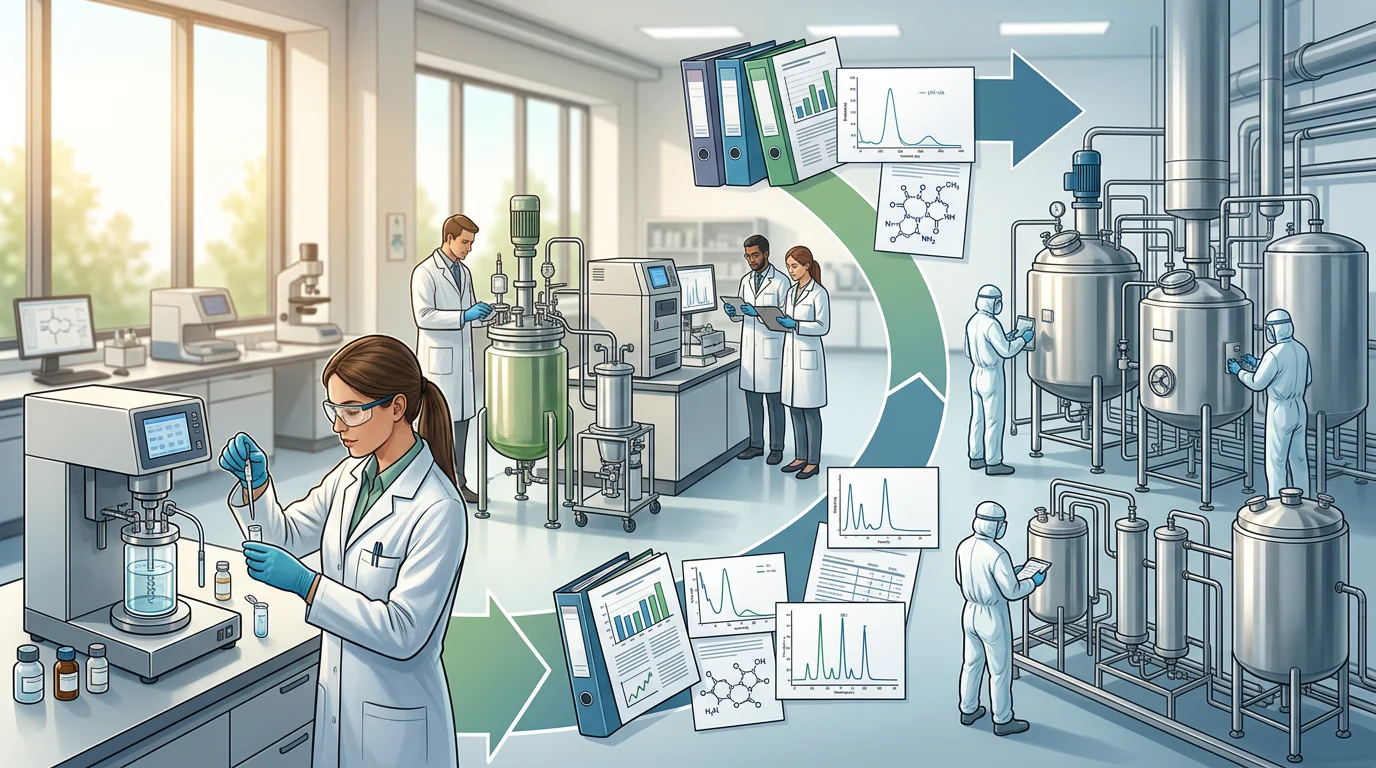
We focus on the impurity profile as well as assay and headline purity. FDA API guidance states that an API impurity profile should be established and compared with submission or historical data at appropriate intervals to detect changes from materials, equipment, or process modifications.
A practical programme includes a process knowledge report, analytical-transfer protocol, scale-up risk assessment, comparability plan, raw-material strategy, and change-control procedure. Teams sourcing for the United States can pair this approach with our US peptide sourcing guidance when planning quality and import requirements.
How Should Pharmaceutical Companies Compare Peptide CDMOs?
We recommend issuing one evidence-led RFI to every candidate rather than accepting each supplier’s preferred presentation format. This makes it easier to compare clinical fit, commercial headroom, analytical depth, quality systems, and transfer accountability on the same basis.
Use a Six-Step RFI Process
- Define clinical phase, target markets, dose, annual demand range, and needed delivery date.
- Describe sequence complexity, modifications, conjugation needs, potency considerations, and target purity.
- Request minimum charged scale, minimum final GMP API quantity, purification limits, and maximum verified campaign output.
- Ask for analytical methods, impurity characterization, stability support, and reference-standard controls.
- Require a written clinical-to-commercial transfer model and a change-control responsibility map.
- Score regulatory support, supply continuity, lead-time assumptions, and total cost drivers without relying on unsupported price estimates.
Cost depends on product-specific factors such as sequence length, modified building blocks, crude yield, purification cycles, analytical work, containment, campaign size, and documentation scope. We therefore avoid publishing generic prices that could mislead a development team.
For India-based sourcing, we encourage buyers to compare peptide evidence separately from broader API capacity. Our Indian API landscape resource can support the broader procurement review, while the RFI should keep peptide-specific manufacturing and control evidence at its center.
Work with Aarise Pharma
At Aarise Pharma, we help procurement and development teams turn an incomplete supplier search into an evidence-based RFI. We start with the product, not a generic facility label: intended phase, target markets, dose strength, projected demand, sequence complexity, route, impurity risks, and required documentation. We then help you organize the questions that determine whether a proposed clinical batch can become a registration and commercial process without avoidable rework. Our role is to make the comparison practical, with clear requests for batch-scale evidence, analytical ownership, quality documentation, change control, and supply planning. If your programme needs peptide API sourcing support, use our API supplier overview alongside the scorecard in this guide, then tell us which evidence you need us to help evaluate. We will respond with a focused discussion of available documentation and next decisions, not unsupported claims. Contact Aarise Pharma
FAQs on Clinical-to-commercial Peptide CDMOs
What Makes a Peptide CDMO Suitable for Clinical-To-Commercial Supply?
We select a CDMO when it can make the required GMP clinical batch, maintain quality attributes through scale-up, and document analytical, quality, and change responsibilities.
How Small Can a GMP Clinical Peptide Batch Be?
We assess fit using required isolated GMP API, purification loading, release testing, stability retains, and practical suite limits, rather than broad capacity claims or reactor volume.
Why Does Analytical Transfer Matter During Scale-Up?
We use analytical transfer to confirm methods distinguish product, impurities, and degradants after changes, helping teams identify comparability risks before confident filing or commercial launch.
Do Public Reactor Volumes Prove Commercial Peptide Capacity?
We do not treat reactor volume as proof because final API output also depends on synthesis yield, purification recovery, isolation, equipment availability, quality release, and supply readiness.


